
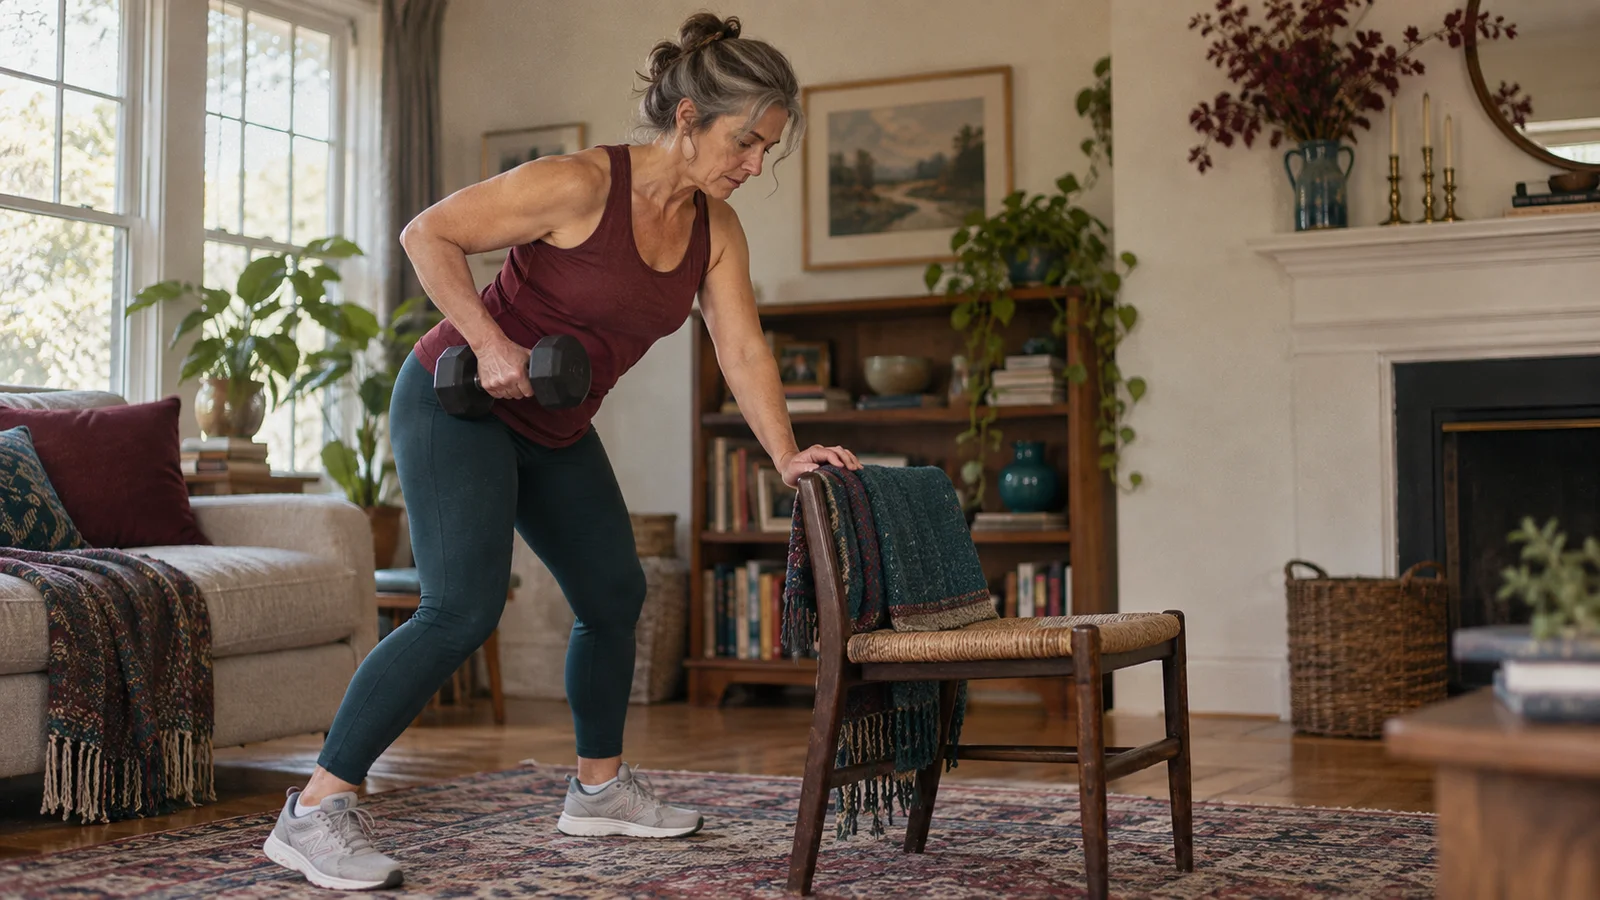
A number on the scale can be remarkably persuasive. It moves, the jeans loosen and suddenly the plan appears to be working. But bodies do not lose only one kind of tissue. During weight loss—including weight loss with GLP-1 medicines—some lean mass can be lost along with fat.
For women in and after the menopause transition, that deserves attention. Muscle is not just an aesthetic category. It supports balance, bones, glucose regulation and the ability to carry groceries, get off the floor and remain independent later.
The evidence is promising—and still developing
GLP-1 medications can produce meaningful weight loss and improve health measures for appropriate patients. Reviews focused on peri- and postmenopausal women also point out an important limitation: this population has not been studied as thoroughly as the enthusiasm surrounding the drugs might suggest.
Research reviews report that lean-body-mass declines can occur during treatment, while the longer-term consequences for strength and function are still being clarified. Lean mass is not identical to muscle, and a scan cannot tell the whole story. But the signal is strong enough to make muscle preservation part of the treatment conversation—not an afterthought once the weight is gone.
A lower number is useful only if the life inside it still works well.
Resistance training is not punishment
You do not need to become a gym person with a shaker bottle and an opinion about macros. Resistance work can mean dumbbells, machines, bands, body-weight movements or repeatedly practicing the tasks you want to keep doing. The National Institute on Aging notes that strength training helps maintain muscle and physical function as we age.
The right starting point depends on your health, experience and joints. A clinician or qualified professional can help adapt movement after injury, surgery or a long break. Consistency and progression matter more than performing fitness.
Eating enough still matters
Because these medications can substantially reduce appetite, some people find it difficult to eat enough protein and nutrient-dense food. Nausea or other gastrointestinal effects can make that harder. Rather than copying a protein target from social media, ask what is appropriate for your body, kidney health, total intake and activity.
A useful check-in covers hydration, constipation or nausea, the pace of weight change, what you can tolerate eating and whether daily tasks feel easier or harder. If your energy falls sharply, you feel weak or you cannot maintain adequate nutrition, contact the prescribing clinician.
Build a function-first follow-up
Before treatment, write down a few baseline abilities: how many times you can rise from a chair comfortably, whether you can carry two bags up the stairs, how far you walk without needing to stop. These are not diagnostic tests. They are real-life markers that may reveal something the bathroom scale misses.
If a GLP-1 is helping, this is not an argument to stop it. It is an argument to make the plan more complete: medication when appropriate, nutrition you can sustain, resistance work you can repeat and follow-up that treats your future strength as an outcome worth protecting.
Editorial note: This article is general education, not medical or nutritional advice. GLP-1 medicines require individualized prescribing and monitoring. Discuss treatment changes and new symptoms with a qualified clinician.
Sources
Review: GLP-1 receptor agonists in peri- and postmenopausal women
Review: GLP-1 therapy, lean mass and postmenopausal health
National Institute on Aging: Strength training and healthier bodies